
Reconstructive Surgery
Cancer surgery removes disease. Reconstruction helps rebuild life afterwards.
Reconstruction planned together with tumour removal to support speech, swallowing, breathing, facial form and rehabilitation.
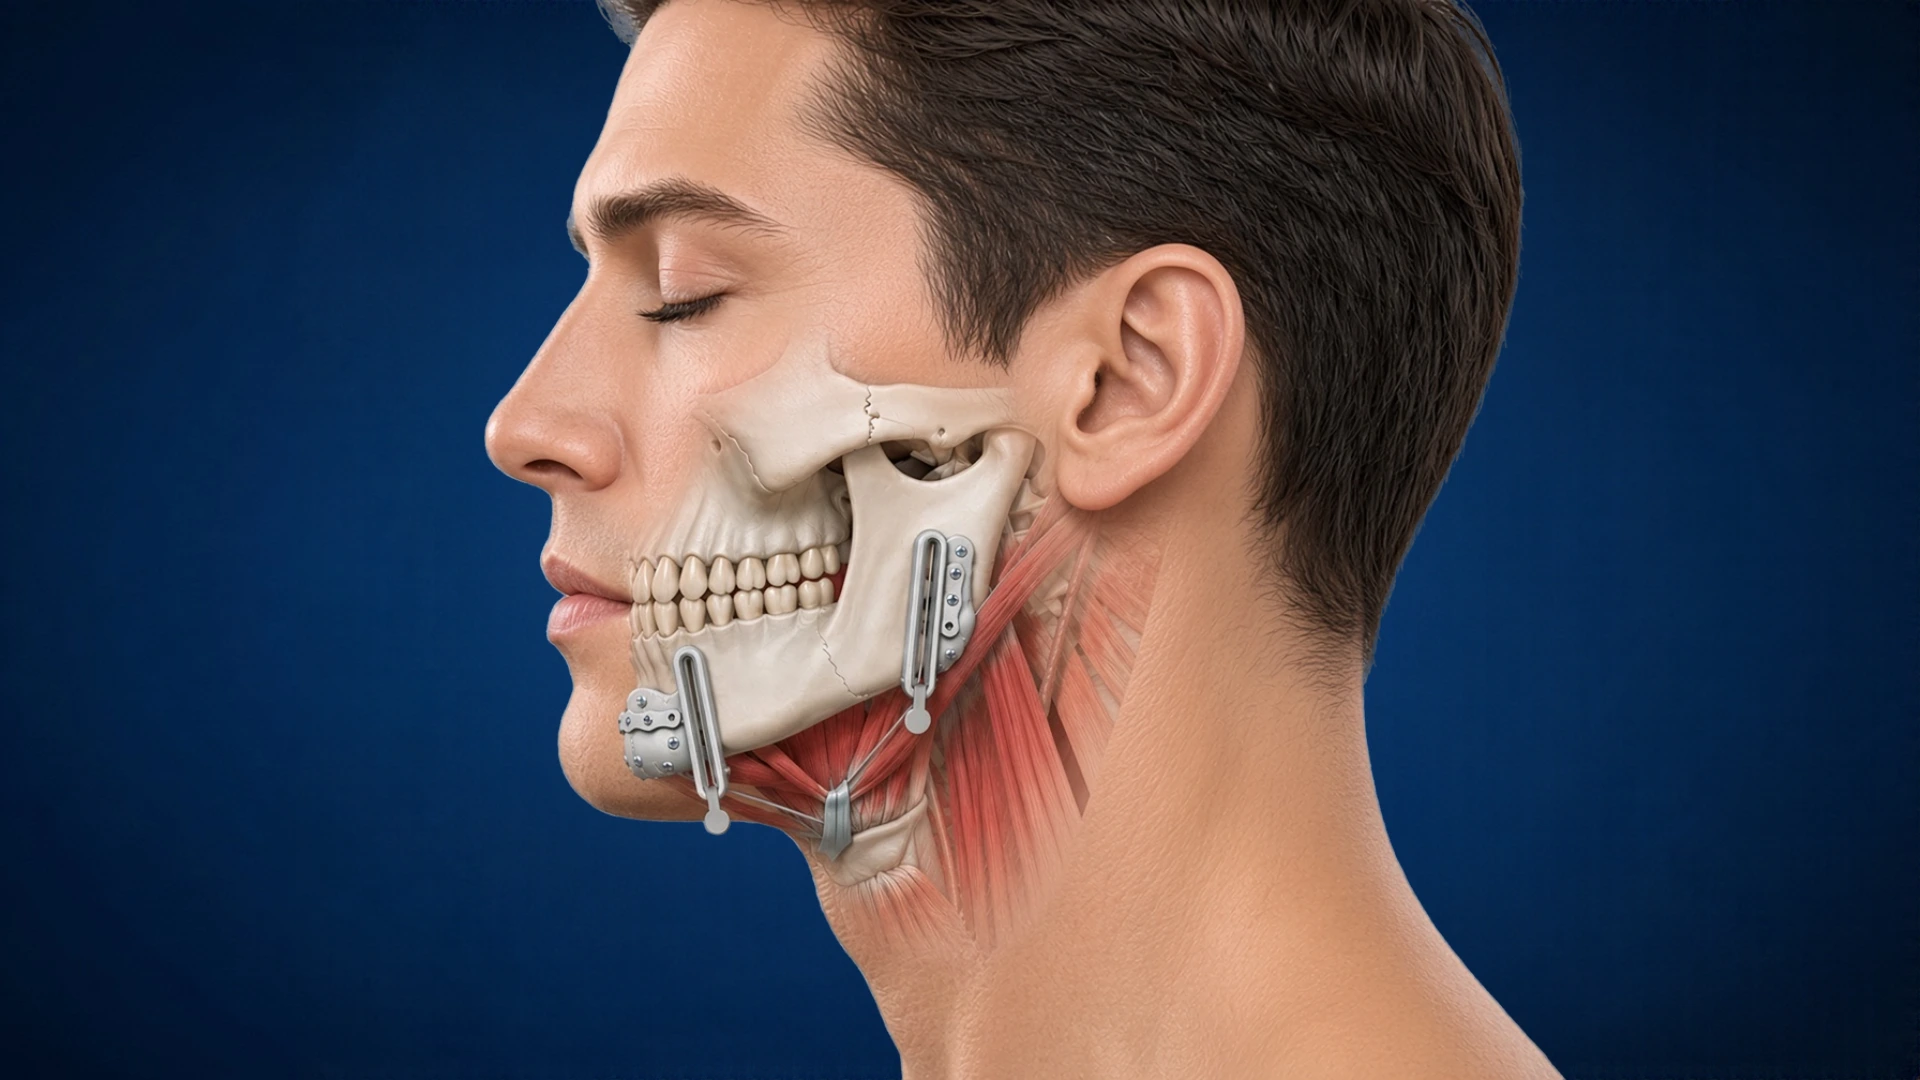
Cancer surgery removes disease. Reconstruction helps rebuild life afterwards.
Head and neck cancers can affect structures responsible for speaking, eating, swallowing, breathing and facial expression.
Removing a cancer can therefore leave a defect that needs more than simple wound closure. Reconstructive surgery becomes part of the cancer treatment itself.
PLANNED BEFORE RESECTION
Reconstruction begins before the tumour is removed.
- What tissue will be removed?
- What function could be lost?
- Does the defect need skin, muscle, bone—or a combination?
- How will reconstruction affect speech and swallowing?
- Will future dental rehabilitation be needed?
What can be reconstructed?
Reconstruction may be required after removal of cancers involving the tongue, cheek, floor of mouth, jaw, throat, facial skin or other head and neck structures.
Bone, muscle and/or skin can be transferred with their blood supply to rebuild areas affected by cancer surgery.
THE RECONSTRUCTIVE LADDER
Not every patient requires a free flap.
01
Primary closure
Smaller defects can sometimes be closed directly.
02
Local tissue reconstruction
Nearby tissue can be rearranged to cover selected defects.
03
Regional flaps
Tissue from a neighbouring area can be transferred while retaining its blood supply.
04
Microvascular free-flap reconstruction
For larger defects, tissue and its blood vessels are transferred and connected to vessels in the neck using microsurgical techniques.
Rebuilding soft tissue
Soft-tissue reconstruction may be needed after removal of part of the tongue, cheek or throat. The aim is not simply to fill a space; the tissue must help provide appropriate shape, mobility, separation of spaces and swallowing function.
Rebuilding the jaw
When part of the mandible must be removed, bone reconstruction may be necessary. In selected patients, bone-containing free flaps can restore jaw continuity and provide a foundation for longer-term oral and dental rehabilitation.
FUNCTION IS THE REAL MEASURE
Reconstruction is judged by life after healing.
- Can the patient swallow safely?
- Can they communicate effectively?
- Can they return to oral feeding?
- Is facial form restored appropriately?
- Can dental rehabilitation be considered?
- What is their quality of life?
Rehabilitation completes the operation
Recovery can involve surgeons, speech and swallowing therapists, dietitians, physiotherapists, dental specialists and oncology teams.
Reconstruction creates the physical foundation. Rehabilitation teaches the reconstructed system how to function.
COMMON QUESTIONS
Questions about reconstructive surgery
General information to help you prepare. A consultation is required for advice about an individual diagnosis or treatment plan.
Does every reconstruction require a free flap?
No. Reconstruction ranges from direct closure and local tissue rearrangement to regional flaps and microvascular free-flap transfer, depending on the defect.
What tissues can be used for reconstruction?
Depending on the need, reconstruction may use skin, soft tissue, muscle, bone or a combination, with or without microsurgical blood-vessel connection.
Why is reconstruction planned before tumour removal?
Planning both parts together helps anticipate the defect, protect function and select an appropriate reconstructive method.
What happens after reconstruction?
Healing is followed by rehabilitation focused on speech, swallowing, nutrition, movement and other functions affected by treatment.
Planning a complex head and neck cancer operation?
A complete plan should explain both what must be removed and how function will be supported afterwards.
